


Clinical Characteristics
Ocular Features
Stargardt disease or fundus flavimaculatus is a progressive form of juvenile macular degeneration with considerable clinical and genetic heterogeneity. It may be considered a syndromal cone-rod dystrophy because of overlapping clinical features such as loss of color vision and photophobia in some patients. Adding to the confusion is the fact that mutations in at least 4 genes are responsible for similar clinical characteristics. Due to the lack of diagnostic distinctions and the wide range of nonspecific clinical manifestations, Stargardt disease and fundus flavimaculatus are discussed here as a single entity.
Onset of vision loss is often noted late in the first decade of life usually with rapid progression. However, some patients are asymptomatic until much later, even into the fifth decade. There is evidence that patients with an early onset have a worse prognosis compared to those with a later onset. Nevertheless, large series of patients contain at least 23% with 20/40 or better acuity, about 20% with 20/50 -20/100, 55% have 20/200-20/400, and a small number have vision less than 20/400.
Some color discrimination is lost and photophobia may be a complaint. Dark adaptation is prolonged but nightblindness does not usually occur and peripheral visual fields are normal. The posterior pole characteristically has yellowish pisciform, round, and linear subretinal lipofuscin deposits which often extend to the equator. These may be present before clinical symptoms are present. Histopathology reveals accumulations of this material in RPE cells. Atrophy of the RPE in the same region is often visible as well but these changes may be subtle initially. Some patients have peripheral pigment clumping which may resemble the bone spicule configuration seen in retinitis pigmentosa. However, retinal vessel caliber is normal in Stargardt disease. Extensive macular disease can be associated with temporal pallor of the optic nerve. The ERG shows reduced photopic responses with normal or near normal scotopic tracings. Fluorescein angiography often reveals more extensive disease than seen on fundoscopy. Window defects are common in the macula where the RPE is atrophied. The flecks may be hypo- or hyperfluorescent. Over 50% of patients have patches of angiographically dark choroid in the posterior pole which is thought to be secondary to transmission blockage by lipofuscin accumulations in the RPE.
Systemic Features
None.
Genetics
Inheritance
This group of disorders may be caused by mutations in at least 4 genes. These are: STGD1 (248200) caused by mutations in the ABCA4 gene located at 1p22.1, or in CNGB3 (262300) (8q21-q22) which also is mutant in achromatopsia 3 (ACHM3), STGD3 (605512) caused by mutations in the ELOVL4 gene at 6q14, and STGD4 (603786) caused by a mutation in PROM1 on chromosome 4p. STGD4 and STGD3 disease have been found in pedigrees consistent with autosomal dominant inheritance but STGD1 disease seems to be inherited in an autosomal recessive pattern.
Genotyping is necessary for accurate diagnostic determinations. In particular, a few patients clinically found to have typical areolar macular dystrophy, retinitis pigmentosa, juvenile macular degeneration, and cone dystrophies have been reported in association with several of these mutations and reports have also associated Stargardt disease with mutations in RDS.
A single family with a brother and sister with Stargardt disease and neurological malformations has been reported (612948). Both had developmental delays associated with absence or hypoplasia of the corpus callosum, upslanted lid fissures, ‘flared eyebrows’, a broad nasal tip, a broad face with a pointed chin, and sensorineural hearing loss along with mild digital malformations. Evidence of macular degeneration was seen at age 7 years and vision in both individuals was in the 20/100-20/200 range. No associated locus or mutation has been identified.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
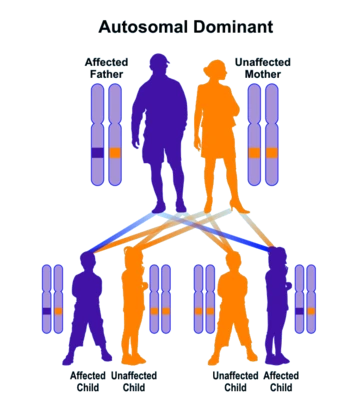
Autosomal dominant inheritance leads to a vertical pattern of transmission
Autosomal recessive
In order for autosomal recessive disorders to be expressed, offspring generally must inherit two mutations, one from each carrier parent. Carriers with only one mutation, such as the parents, do not have clinical disease. Note that carrier parents can expect that 1 in 4 children (25%) will inherit both mutations and have the disorder, 2 in 4 children (50%) will be carriers like their parents, while 1 in 4 children (25%) inherit neither mutation.

In order for autosomal recessive disorders to be expressed, offspring generally must inherit two mutations, one from each carrier parent. Carriers with only one mutation, such as the parents, do not have clinical disease. Note that carrier parents can expect that 1 in 4 children (25%) will inherit both mutations and have the disorder, 2 in 4 children (50%) will be carriers like their parents, while 1 in 4 children (25%) inherit neither mutation.